
The association between clinical activity and inflammatory response in odontogenic keratocysts. A retrospective study
Журнал: Российская стоматология. 2026;19(3):13-17. (Статья на английском языке.)
DOI: 10.17116/rosstomat20261903113
Read: 262 раза
Abstract
BACKGROUND AND AIM
Secondary Inflammation in odontogenic keratocyst induces odontogenic epithelial lining to lose its characteristic features by initiating the proliferation of epithelial cells. This can have an indirect impact on clinical aggressiveness. The aim of the present study is to retrospectively evaluate the association of inflammatory cell infiltrate and the clinical aggressiveness of odontogenic keratocyst.
MATERIALS AND METHODS
n=45 cases of OKC were analysed histopathologically for its type and for the amount and distribution of inflammatory cell infiltrate. The data were tabulated and exported to IBM SPSS statistics software. Pearson Chi-square test was done to analyse the association between the inflammation and clinical aggressiveness.
RESULT
71.1% of the OKC cases turned out to show chronic inflammatory cell infiltrate. 88.8% of the cases with hyperplastic epithelial lining showed moderate to severe inflammatory cell infiltrate (p=0.05). A statistical significance (p=0.019) was obtained between the type of inflammatory cell infiltrate and the clinical aggressiveness. The OKCs with clinical aggressiveness showed a chronic to mixed inflammatory cell infiltration. A statistical significance was also obtained (p=0.023) between the amount of inflammatory cell infiltrate and the clinical aggressiveness.
CONCLUSION
In the present study, the clinical aggressiveness of the OKCs were significantly associated with the type and amount of inflammatory cell infiltrate. However, more elaborate studies with advanced immunohistochemical markers, molecular techniques and increased sample size, are required to firmly establish the association.
Keywords
- clinical aggressiveness
- inflammation
- odontogenic keratocyst
- association
Дата поступления: 19.09.2024
Дата принятия в печать: 23.01.2025
Дата публикации: 22.09.2026
Introduction
The odontogenic keratocyst (OKC) was established as a separate pathologic entity in 1956 by philipsen and this developmental entity makes up about 11.2% of all the odontogenic cysts [1]. OKC is unique among the other odontogenic cysts because of its distinct histologic characteristics and high recurrence rate [2—4]. The clinical aggressiveness and recurrence of OKCs have been a topic of study in literature previously [5, 6]. The presence of non-keratinized odontogenic epithelial lining, and its intense proliferative activity to form rete ridges and occasional arcading patterns are the main histological features of inflamed OKCs, which makes them indistinguishable from the other odontogenic cysts which are secondarily infected [7].
The proliferative potential of odontogenic keratocystic lining secondary to inflammation and the influence of this inherent growth potential of this epithelial lining on the recurrence rate of OKC were also reported previously in literature [8—10]. The tendency of the epithelial cells to lose its characteristic features upon secondary inflammation and an increase in the expression of ki-67 and PCNA labeling index in metaplastic epithelium in areas with moderate to severe inflammation were studied previously by Benn et al in 1996 and Kaplan et al in 2004 [1, 11]. In addition, Smith g et al found that a substantial number of chronic inflammatory cell infiltrate, particularly the mast cells in the subepithelial connective tissue wall can play an important role in cyst enlargement [12]. Several immunohistochemical studies also showed an intricate relation between the inflammation and epithelial proliferation in OKC and thereby correlating the inflammation and clinical aggressiveness [13—16]. The aim of the present study is to retrospectively evaluate the association of inflammatory cell infiltrate and clinical aggressiveness of odontogenic keratocyst.
Materials and methods
This study was conducted with approval from the institutional ethics committee and included n=45 cases of OKC reported to the department of oral and maxillofacial pathology, blinded for peer review. The demographic and clinical details of the selected cases were retrieved from the histopathology reports and common clinical database. Cases with questionable and nonspecific histopathological diagnosis were excluded and only histopathologically confirmed cases of OKC were included in the present study. Slides of the selected cases were retrieved from the oral pathology department archives. Histopathological analysis of inflammation in OKC was done by two independent pathologists and the details regarding the clinical measurement of the lesions were obtained from the common clinical database.
The various criterias used to assess the clinical size of OKC and the histopathological assessment of inflammation is given in table 1 (Table 1). Based on these criterias, 45 cases of OKC were analysed histopathologically for inflammatory cell infiltrate. All the demographic, clinical, histopathological details were tabulated in Microsoft Excel and later exported into IBM SPSS statistics software. Pearson Chi-square test was done to analyse the association between the inflammation and clinical aggressiveness and p values less than 0.05 is considered as statistically significant.
Table 1. Showing the criteria of assessing the clinical aggressiveness and the histopathological evaluation of inflammation in OKC
Clinical aggressiveness | Small <2cm |
|---|---|
Moderate 2—5 cm | |
Large >5 cm | |
Type of inflammatory cell infiltrate | Acute |
Chronic | |
Amount of inflammatory cell infiltrate | Mild |
Moderate | |
Severe | |
Distribution of inflammatory cell infiltrate | Localised |
Diffused |
Results
71.1% of the OKC cases selected showed chronic inflammatory cell infiltrate followed by mixed (24.4%). Moderate to severe inflammation was seen in 71.1% of the cases and Diffused pattern of distribution (64.4%) of inflammatory cells is more commonly seen than localized. On assessing the clinical aggressiveness, moderately aggressive lesions were more common (Table 2).
Table 2. Showing the percentage of the type, amount and distribution of inflammatory cell infiltrate and the clinical aggressiveness of the OKC cases included in the study
Inflammatory cell infiltrate — Type, % | Acute | 4.4 |
|---|---|---|
Chronic | 71.1 | |
Mixed | 24.4 | |
Inflammatory cell infiltrate — Amount, % | Mild | 28.9 |
Moderate | 53.3 | |
Severe | 17.8 | |
Inflammatory cell infiltrate — Distribution, % | Localised | 35.6 |
Diffused | 64.4 | |
Clinical Aggressiveness, % | Small | 31.1 |
Moderate | 42.2 | |
Large | 26.7 |
Among all the cases, 45% of the cases in which the epithelial lining lost its characteristic appearance and became proliferative and non-keratinized. In 88.8% of the cases with hyperplastic epithelial lining showed moderate to severe inflammatory cell infiltrate in connective tissue wall (p=0.05). The association between the clinical aggressiveness and type of inflammatory cell infiltrate was found to be statistically significant (p=0.019) (Table 3) and the OKCs with a clinical aggressive course showed more of a chronic to mixed inflammatory cell infiltration rather than acute inflammation (Fig. 1). The amount of inflammatory cell infiltrate and the clinical aggressiveness also showed statistically significant association (p=0.023) (Fig. 2).
Table 3. Showing the association between clinical aggressiveness and inflammation in OKC
Variables | p-value (Chi-square test) | |
|---|---|---|
Inflammatory cell infiltrate — Type | Clinical Aggressiveness | *.019 |
Inflammatory cell infiltrate — Amount | Clinical Aggressiveness | *.023 |
Inflammatory cell infiltrate — Amount | Epithelial lining morphology | 0.05 |
Inflammatory cell infiltrate — Distribution | Clinical Aggressiveness | 0.206 |
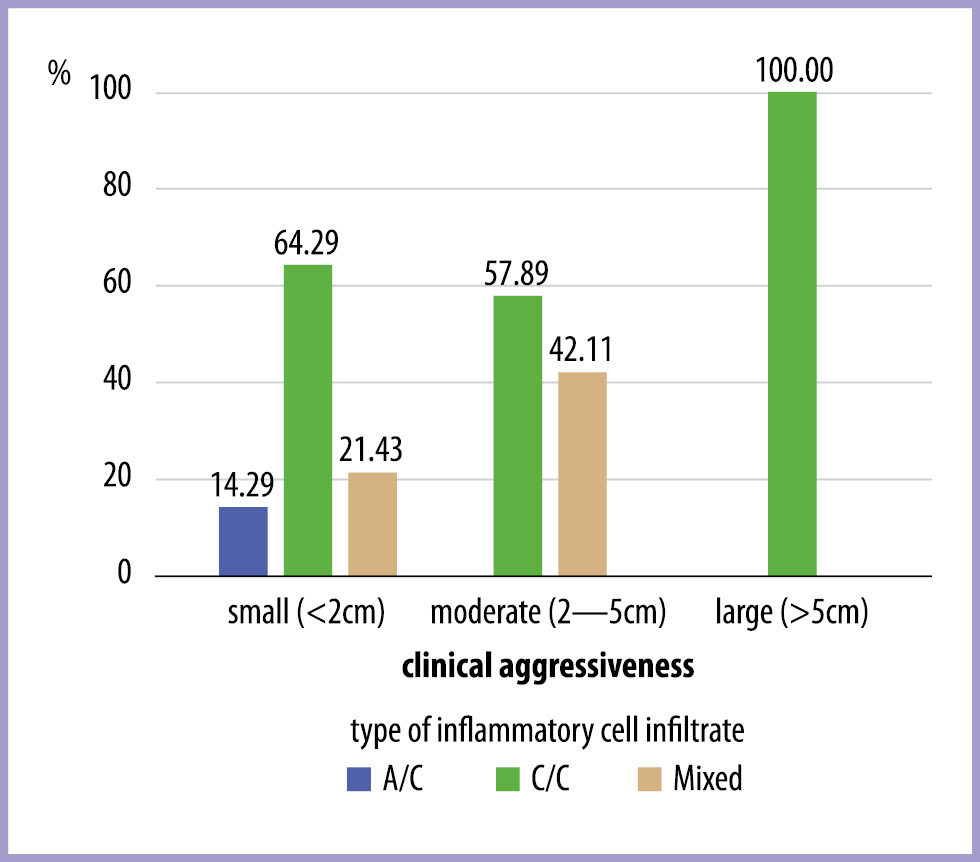
Fig. 1. Bar graph showing the association of type of inflammatory cell infiltrate and clinical aggressiveness. Chi-square test-p value = 0.019. Chronic to mixed inflammatory cell infiltrate were more associated with clinically aggressive OKCs.
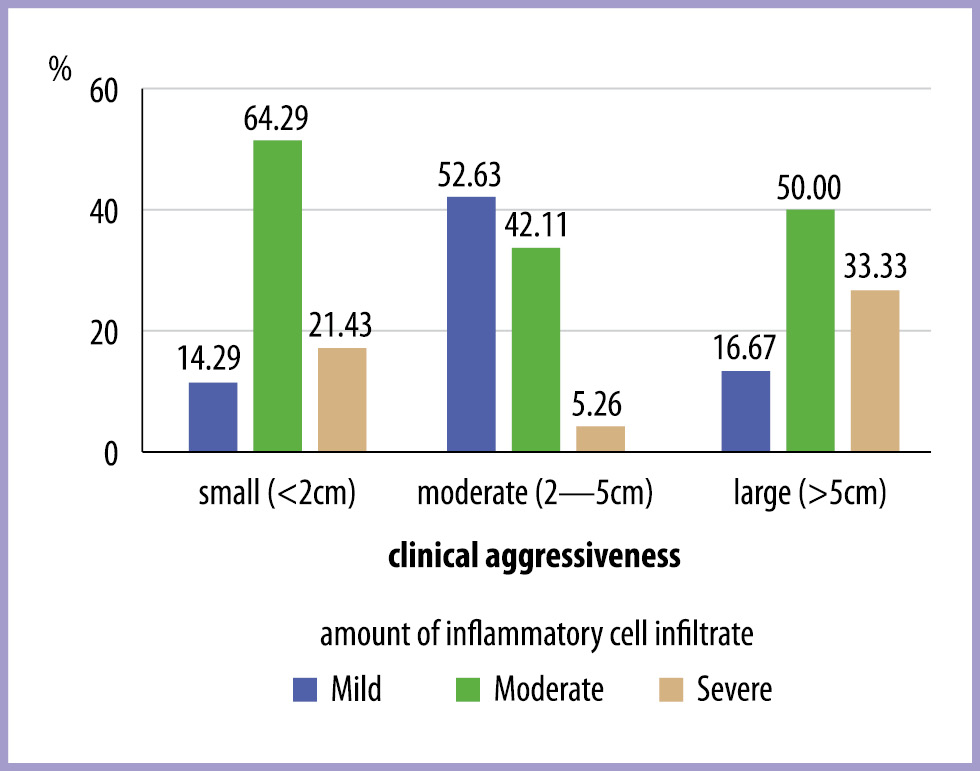
Fig. 2. Bar graph showing the association of amount of inflammatory cell infiltrate and clinical aggressiveness. Chi-square test-p value = 0.023. Moderate to severe inflammation is predominantly seen in clinically aggressive OKCs.
Discussion
OKC is a developmental cyst originating from odontogenic epithelium and accounts for 11.2% of all the odontogenic cysts [17]. Philipsen in 1956 proposed OKC as a separate pathologic entity [18]. In WHO 2005 classification of head and neck tumours, OKC has been reclassified and renamed as keratocystic odontogenic tumor (KCOT) because of its increased clinical aggressiveness and high recurrence rates [19]. Later in 2017, WHO classified the keratocystic odontogenic tumor back into the cyst category as OKC [20].
In an uninflamed OKC, the odontogenic epithelial lining is parakeratinized and corrugated with a uniform thickness of 6—10 cell layers and a polarised basal cell layer [21]. The clinical aggressiveness and high recurrence rate of odontogenic keratocyst is due to the presence of satellite cysts, daughter cysts and the flat connective tissue epithelial interface which makes it difficult to remove during surgical enucleation [1]. Thus the remaining fragmented epithelial lining following an improper enucleation procedure by the surgeon can lead to the formation of new cysts [22]. This also suggests the importance of modulation of the proliferation capacity of odontogenic epithelial lining cells and its impact on rate of recurrence and clinical aggressiveness [18].
Even though the OKC is a developmental cyst, most of the reported cases in the literature were inflamed OKC [23—25]. In the present study also, 71.1% of the cases showed chronic inflammatory cells in their connective tissue walls which was in line with the previous literature. Several studies have also found a direct influence of inflammatory cell infiltrate on the epithelial cell proliferation. This inflammation induced hyper proliferative activity of cells o OKC lining correlates with the increased activity of the cystic lining and clinical aggressiveness [1].
The association between the inflammation and proliferation of epithelial lining cells in OKC can be direct and indirect. The direct mechanism is by the adhesion of inflammatory cells to the epithelial lining and the indirect mechanism is by the response of the epithelial cells to a series of chemokines secreted by inflammatory cells [1]. The present study was also in accordance with the same because in 45% of the cases the epithelial lining lost its characteristic appearance and became proliferative and non-keratinized and 88.8% of the cases with hyperplastic epithelial lining showed moderate to severe inflammatory cell infiltrate in their connective tissue wall (p=0.05). This indicates that there could be a direct or indirect association between the inflammation in the connective tissue wall, proliferation capacity of epithelial lining and its morphology. The above mentioned observation in the present study is supported by the observation of Paula et al, in which they established that the positive cell count of cell proliferation markers such as PCNA and Ki-67 is significantly higher in inflamed OKC compared with non-inflamed OKC (16). Apart from Paula et al., Ninomiya et al. and Nakamura et al. also studied expression of Ki 67 in odontogenic cysts [26, 27] but the disparity in thickness of epithelial lining was not taken into account in their studies. However Kaplan et al studied the expression of this proliferation marker in different fields of OKC and found that the inflammation adjacent to the epithelial cyst lining had a localized effect on epithelium which might induce proliferation in the epithelial lining and a focal increase in expression of Ki-67 but not PCNA [1]. However, this association has not been investigated thoroughly in the previous studies and the current study also gives a preliminary light in this area.
The present study also showed a statistically significant relation between the amount of inflammatory cell infiltrate and the clinical aggressiveness (Fig. 3). Among the cases included in the study, 83.3% of the clinically large lesions or clinically aggressive OKCs showed moderate to severe inflammatory cell infiltrate in their connective tissue wall (Fig. 4). This could be due to the induction of epithelial proliferation by intense inflammatory reaction and thereby increasing its aggressiveness. The chronic inflammatory cells like plasma cells, lymphocytes and macrophages were seen associated with more aggressive lesions compared to less aggressive lesions (Fig. 5). This could be explained by production and secretion of growth factors and cytokines such as interleukin-1, interleukin-6 and tumor necrosis factor (TNF) by the chronic inflammatory cells [28—30]. Apart from this, Li et al suggested that the epidermal growth factor expression by odontogenic epithelial lining is related to the presence of inflammation within the connective tissue wall [31]. Even though the present study showed a statistically significant association, the cytokines can have a varied impact on epithelial lining, it can have a positive and negative impact on cell proliferation, which cannot be assessed by the current study. Hence, an extensive study connecting the molecular mechanisms are needed to prove this association in a more scientific form.
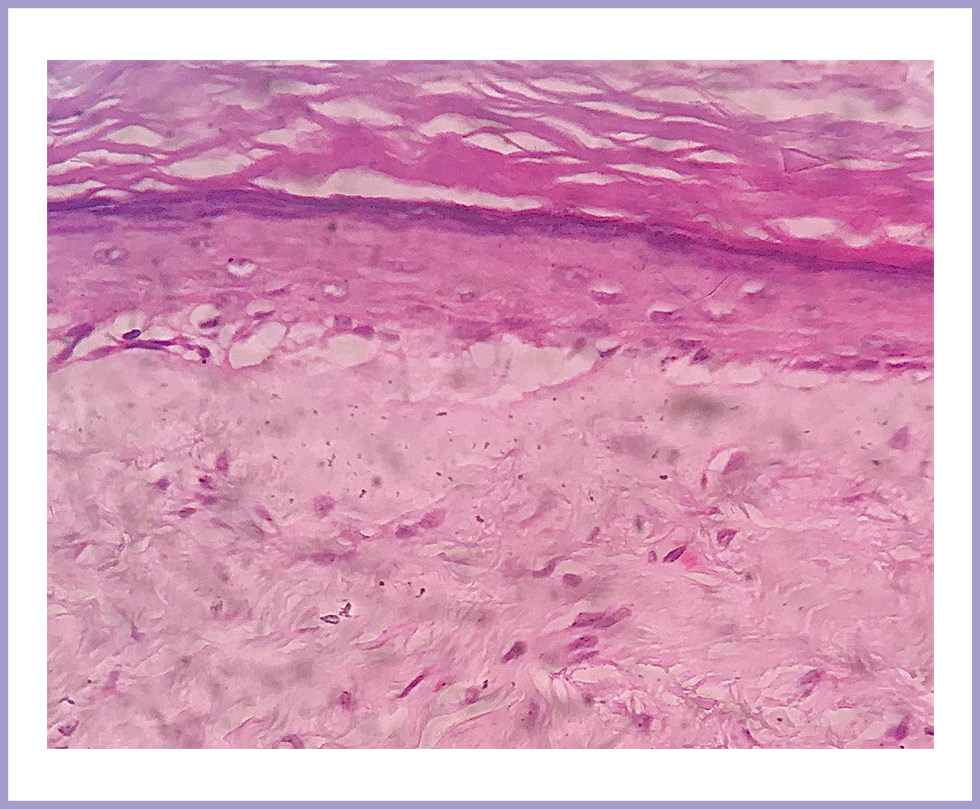
Fig. 3. Orthokeratinized OKC with mild inflammatory cells infiltrate in the connective tissue wall.
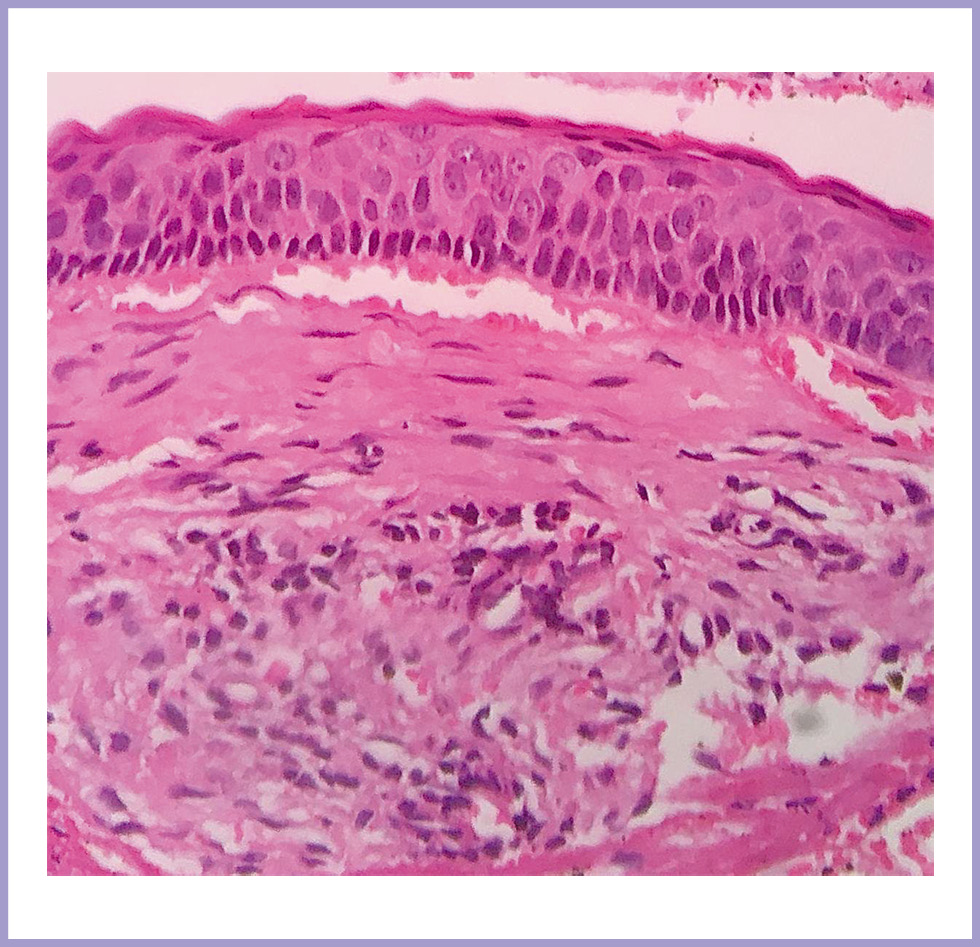
Fig. 4. OKC with moderate chronic inflammatory cells infiltrate in the connective tissue wall and detachment of the epithelial lining from connective tissue wall.
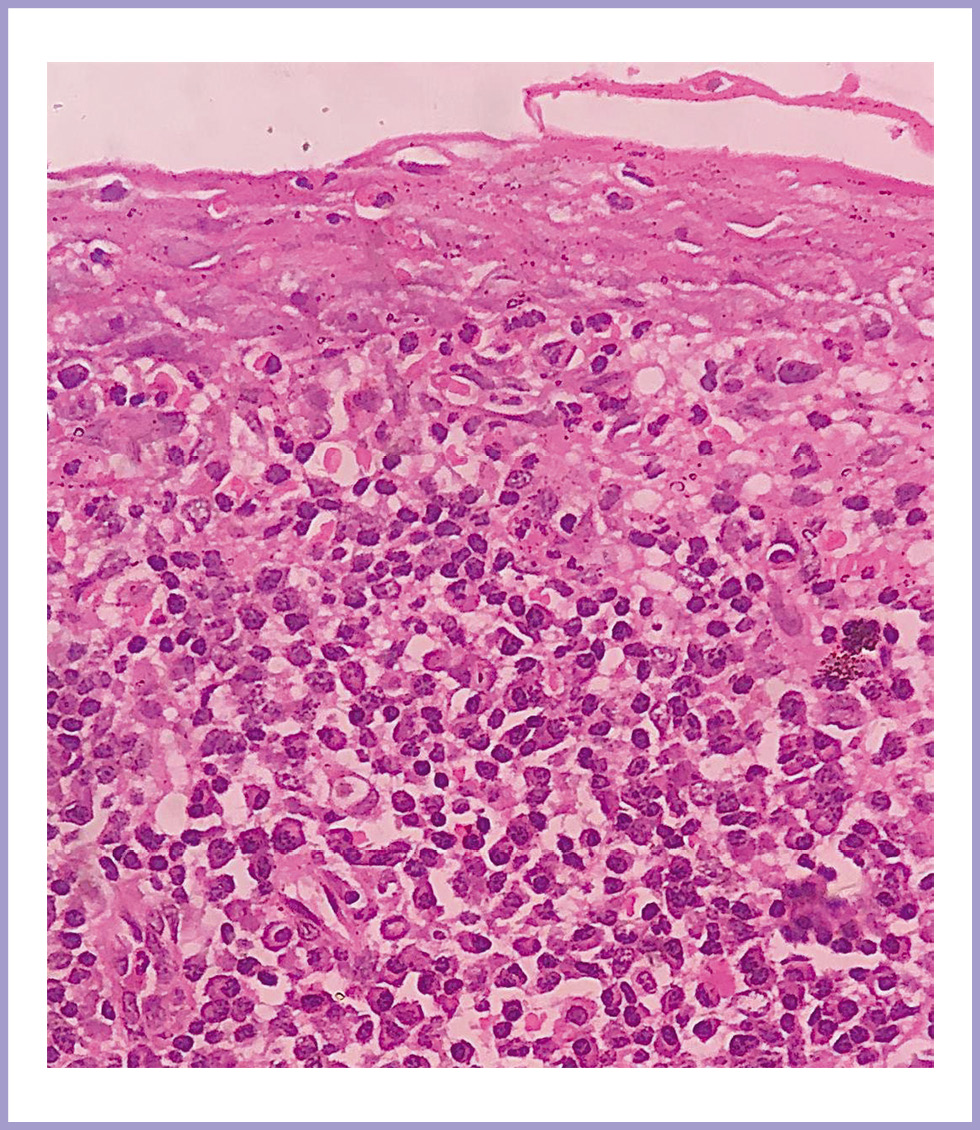
Fig. 5. OKC with intense chronic inflammatory cells infiltrate in the connective tissue wall. The epithelial lining lost its characteristic parakeratin corrugated surface layer and palisaded and columnar basal cell layer.
Lack of recording of inflammation in field specific manner and the less sample size are the main drawbacks of the present study. Immunohistochemical and molecular level studies could better aid in establishing the significant association between the inflammation and clinical aggressiveness and which can further help in the betterment of prognosis of OKC.
Conclusion
However, the present study could establish a statistically significant association between clinical aggressiveness with type and amount of inflammatory cell infiltrate, more futuristic studies with increased sample size, Immunohistochemical and molecular level techniques should be conducted to establish the association.
The authors declare no conflict of interest.
- Kaplan I, Hirshberg A. The correlation between epithelial cell proliferation and inflammation in odontogenic keratocyst. Oral Oncol. 2004 Nov; 40(10):985-991. https://doi.org/10.1016/j.oraloncology.2004.04.017
- Kramer IR, Pindborg JJ, Shear M. The WHO Histological Typing of Odontogenic Tumours. A commentary on the Second Edition. Cancer. 1992 Dec 15;70(12):2988-2994. https://doi.org/10.1002/1097-0142(19921215)70:12<2988::aid-cncr2820701242>3.0.co;2-v
- Shear M, Seward GR. Cysts of the oral regions. John Wright; 1992.
- Shear M. Developmental odontogenic cysts. An update. J Oral Pathol Med. 1994 Jan;23(1):1-11. https://doi.org/10.1111/j.1600-0714.1994.tb00246.x
- Chandrashekar C, Patel P, Thennavan A, Radhakrishnan R. Odontogenic keratocyst: Analysis of recurrence by AgNOR, p53 and MDM2 profiling. J Oral Maxillofac Pathol. 2020 Jan-Apr;24(1):184-185. https://doi.org/10.4103/jomfp.JOMFP_129_19
- Shear M. The aggressive nature of the odontogenic keratocyst: is it a benign cystic neoplasm? Part 2. Proliferation and genetic studies. Oral Oncol. 2002 Jun;38(4):323-331. https://doi.org/10.1016/s1368-8375(01)00066-5
- de Vicente JC, Torre-Iturraspe A, Gutiérrez AM, Lequerica-Fernández P. Immunohistochemical comparative study of the odontogenic keratocysts and other odontogenic lesions. Med Oral Patol Oral Cir Bucal. 2010 Sep 1;15(5):e709-715. https://doi.org/10.4317/medoral.15.e709
- Shear M. The aggressive nature of the odontogenic keratocyst: is it a benign cystic neoplasm? Part 1. Clinical and early experimental evidence of aggressive behaviour. Oral Oncol. 2002 Apr;38(3):219-226.
- Li TJ, Browne RM, Matthews JB. Quantification of PCNA+ cells within odontogenic jaw cyst epithelium. J Oral Pathol Med. 1994 Apr;23(4):184-189. https://doi.org/10.1111/j.1600-0714.1994.tb01110.x
- Li TJ, Browne RM, Matthews JB. Epithelial cell proliferation in odontogenic keratocysts: a comparative immunocytochemical study of Ki67 in simple, recurrent and basal cell naevus syndrome (BCNS)-associated lesions. J Oral Pathol Med. 1995 May;24(5):221-226. https://doi.org/10.1111/j.1600-0714.1995.tb01171.x
- Benn A, Altini M. Dentigerous cysts of inflammatory origin. A clinicopathologic study. Oral Surg Oral Med Oral Pathol Oral Radiol Endod. 1996 Feb; 81(2):203-209. https://doi.org/10.1016/s1079-2104(96)80416-1
- Kumar V, Cotran RS, Robbins SL. Robbins Basic Pathology. Saunders; 2003:873.
- Brown DC, Gatter KC. Ki67 protein: the immaculate deception? Histopathology. 2002 Jan;40(1):2-11. https://doi.org/10.1046/j.1365-2559.2002.01343.x
- Scholzen T, Gerdes J. The Ki-67 protein: from the known and the unknown. J Cell Physiol. 2000 Mar;182(3):311-322. https://doi.org/10.1002/(SICI)1097-4652(200003)182:3<311::AID-JCP1>3.0.CO;2-9
- Paunesku T, Mittal S, Protić M, et al. Proliferating cell nuclear antigen (PCNA): ringmaster of the genome. Int J Radiat Biol. 2001 Oct;77(10):1007-1021. https://doi.org/10.1080/09553000110069335
- de Paula AM, Carvalhais JN, Domingues MG, et al. Cell proliferation markers in the odontogenic keratocyst: effect of inflammation. J Oral Pathol Med. 2000 Nov;29(10):477-482. https://doi.org/10.1034/j.1600-0714.2000.291001.x
- Borghesi A, Nardi C, Giannitto, et al. Odontogenic keratocyst: imaging features of a benign lesion with an aggressive behaviour. Insights Imaging. 2018 Oct;9(5):883-897. https://doi.org/10.1007/s13244-018-0644-z
- Tandon S, Phull K, Tandon P. Pathogenesis of keratocystic odontogenic tumor-A review. TMU J Dent. 2014;3:100-105.
- Passi D, Singhal D, Singh, et al. Odontogenic keratocyst (OKC) or keratocystic odontogenic tumor (KCOT)—Journey of OKC from cyst to tumor to cyst again: comprehensive review with recent updates on WHO classification. Int J Curr Res Rev. 2017;9(7):54080-54086.
- Wright JM, Vered M. Update from the 4th Edition of the World Health Organization Classification of Head and Neck Tumours: Odontogenic and Maxillofacial Bone Tumors. Head Neck Pathol. 2017 Mar;11(1):68-77. https://doi.org/10.1007/s12105-017-0794-1
- Singh H, Shetty D, Kumar, et al. A molecular insight into the role of inflammation in the behavior and pathogenesis of odontogenic cysts. Ann Med Health Sci Res. 2013 Oct;3(4):523-528. https://doi.org/10.4103/2141-9248.122072
- Karaca C, Dere KA, Er N, et al. Recurrence rate of odontogenic keratocyst treated by enucleation and peripheral ostectomy: Retrospective case series with up to 12 years of follow-up. Med Oral Patol Oral Cir Bucal. 2018 Jul 1;23(4):e443-e448. https://doi.org/10.4317/medoral.22366
- el-Hajj G, Anneroth G. Odontogenic keratocysts--a retrospective clinical and histologic study. Int J Oral Maxillofac Surg. 1996 Apr;25(2):124-129. https://doi.org/10.1016/s0901-5027(96)80057-9
- Rodu B, Tate AL, Martinez MG. Jr. The implications of inflammation in odontogenic keratocysts. J Oral Pathol. 1987 Nov;16(10):518-521. https://doi.org/10.1111/j.1600-0714.1987.tb00684.x
- Kakarantza-Angelopoulou E, Nicolatou O. Odontogenic keratocysts: clinicopathologic study of 87 cases. J Oral Maxillofac Surg. 1990 Jun;48(6):593-599; disc. 599-600. https://doi.org/10.1016/s0278-2391(10)80472-0
- Ninomiya T, Kubota Y, Koji T, Shirasuna K. Marsupialization inhibits interleukin-1alpha expression and epithelial cell proliferation in odontogenic keratocysts. J Oral Pathol Med. 2002 Oct;31(9):526-533. https://doi.org/10.1034/j.1600-0714.2002.00029.x
- Nakamura N, Mitsuyasu T, Mitsuyasu, et al. Marsupialization for odontogenic keratocysts: long-term follow-up analysis of the effects and changes in growth characteristics. Oral Surg Oral Med Oral Pathol Oral Radiol Endod. 2002 Nov;94(5):543-553. https://doi.org/10.1067/moe.2002.128022
- Greenhalgh DG. The role of growth factors in wound healing. J Trauma. 1996 Jul;41(1):159-167. https://doi.org/10.1097/00005373-199607000-00029
- Bando Y, Henderson B, Meghji, et al. Immunocytochemical localization of inflammatory cytokines and vascular adhesion receptors in radicular cysts. J Oral Pathol Med. 1993 May;22(5):221-227. https://doi.org/10.1111/j.1600-0714.1993.tb01060.x
- Torabinejad M. Mediators of acute and chronic periradicular lesions. Oral Surg Oral Med Oral Pathol. 1994 Oct;78(4):511-521. https://doi.org/10.1016/0030-4220(94)90046-9
- Li TJ, Browne RM, Matthews JB. Expression of epidermal growth factor receptors by odontogenic jaw cysts. Virchows Arch A Pathol Anat Histopathol. 1993;423(2):137-144. https://doi.org/10.1007/BF01606588



Recommended articles:
Endometriosis as a fibroinflammatory disease: enzyme therapy in comprehensive management. An Expert Council Resolution.Russian Journal of Human Reproduction. 2026;32(4):18-31
Micro- and nanoplastic as new modifiable cardiovascular risk factors.Russian Journal of Preventive Medicine. 2026;29(8):113-117
The importance of proteolytic systems in the diagnosis and prognosis of neurodegenerative diseases associated with protein degradation disorders (literature review).Laboratory Service. 2026;15(2):31-36
Association of single-nucleotide variants of ABCG2 and ABCB1 genes with clinical and laboratory parameters during clozapine therapy.S.S. Korsakov Journal of Neurology and Psychiatry. 2026;126(4):77-80
Alopecia areata morbidity structure considering the association with atopic dermatitis in the population of Moscow in comparison with data from the federal register.Russian Journal of Clinical Dermatology and Venereology. 2026;25(2):169-177
Impaired reparative regeneration in patients with acute appendicitis.Pirogov Russian Journal of Surgery. 2026;(2):73-84
The role of the human gut microbiota in the phenotypic age determination.Russian Journal of Preventive Medicine. 2026;29(1):74-80
Relationship of circulating caspases-1 and -8, their ratio with coronary artery atherosclerosis.Russian Journal of Preventive Medicine. 2026;29(1):40-46
Experience of using mineral waters in patients with type 1 diabetes mellitus for the correction of endotoxinemia.Problems of Balneology, Physiotherapy and Exercise Therapy. 2025;102(6):26-31
Endogenous and exogenous succinate: what is significant functional difference? Or is it not?Russian Journal of Anesthesiology and Reanimatology. 2025;(6):125-131