
- Media Sphera
- Publishers





Introduction
Duodenal perforation (DP) is considered a life-threatening injury. These injuries are reported in 4.3% of patients with abdominal trauma, with mortality rates ranging from 5.3% to 30% [1, 2]. DP is a type of polyetiologic lesion that occurs in patient with gastric and duodenal ulcer disease and is iatrogenic or posttraumatic in origin. CT with intravenous and oral contrast plays a key role in the diagnosis of DP [3, 4]. Treatment directly depends on the cause, duration, location, nature and general condition of the patient. Active conservative treatment under dynamic control is possible in closed or closed lesions and in clinically stable patients [5]. Patients with acute peritonitis, sepsis and intra-abdominal abscess require urgent surgical treatment. In recent decades, minimally invasive endoscopic treatment for DP has been considered an alternative to open surgical treatment [6—8] and is justified in practice.
Case description
A 58-year-old Caucasian woman (K.G., born in 1963) with a history of right-sided nephrolithiasis, terminal hydronephrosis and chronic calculous cholecystitis was initially treated at another medical center. She presented with severe right subcostal and epigastric pain radiating to the right scapula, accompanied by nausea, a bitter taste in the mouth and generalized weakness with elevated blood pressure (Table).
Timeline of diagnostic and therapeutic steps
| Date | Event | Findings/Intervention | Outcome |
| 22.11.2021 | Ultrasound | Thickened gallbladder wall (2.5 mm), gallstones (7.0 mm, 2.6 mm) | Diagnosis: chronic calculous cholecystitis, right nephrolithiasis, terminal hydronephrosis |
| 24.11.2021 | Surgery | Laparoscopic cholecystectomy+right nephrectomy | — |
| 04.12.2021 | Post-op | Fever 38.6 °C, purulent drain output | Conservative treatment started |
| 13.12.2021 | CT scan | 26-mm retroperitoneal mass with air; 4-mm duodenal defect | Percutaneous drainage |
| 17.01.2022 | Labs/CT | Elevated CRP, leukocytes; 22-mm retroperitoneal fluid | Second percutaneous drainage |
| 23.03.2022 | ICU admission | Duodenal perforation, retroperitoneal abscess, sepsis | Intensive care |
| 09.04.2022 | Endoscopy | 0.4×0.6 cm duodenal fistula | TTS endoclips+endoloop closure |
| 01.05.2022 | Follow-up CT | No contrast extravasation; fibrotic tissue | Complete fistula closure confirmed |
The initial (22.11.2021) diagnostic ultrasound revealed a thickened gallbladder wall (2.5 mm) and multiple gallstones (7.0 mm and 2.6 mm). A diagnosis of chronic calculous cholecystitis, right-sided nephrolithiasis and terminal hydronephrosis was made.
After a short preoperative preparation (23.11.2021), a «laparoscopic cholecystectomy» (LCE) and a one-stage «laparoscopic right-sided nephrectomy» were performed the next day under multicomponent intravenous anaesthesia with endotracheal intubation.
On postoperative day 10, the patient developed a fever of 38.6 °C, along with general weakness and malaise, and purulent discharge was observed from the intraperitoneal drain. She received prolonged conservative management, including antibiotic therapy and supportive care.
A CT scan performed on 13.12.2021 revealed a 26-mm mass with air bubbles in the right retroperitoneal region, along with edema and infiltration of the surrounding adipose tissue. A 4-mm defect was identified in the right posterolateral wall of the second duodenal segment, with contrast extravasation into the retroperitoneal mass. Thickening of the adjacent peritoneal layers was also noted (Fig. 1). The patient underwent percutaneous drainage of the right retroperitoneal space and was discharged for outpatient care.
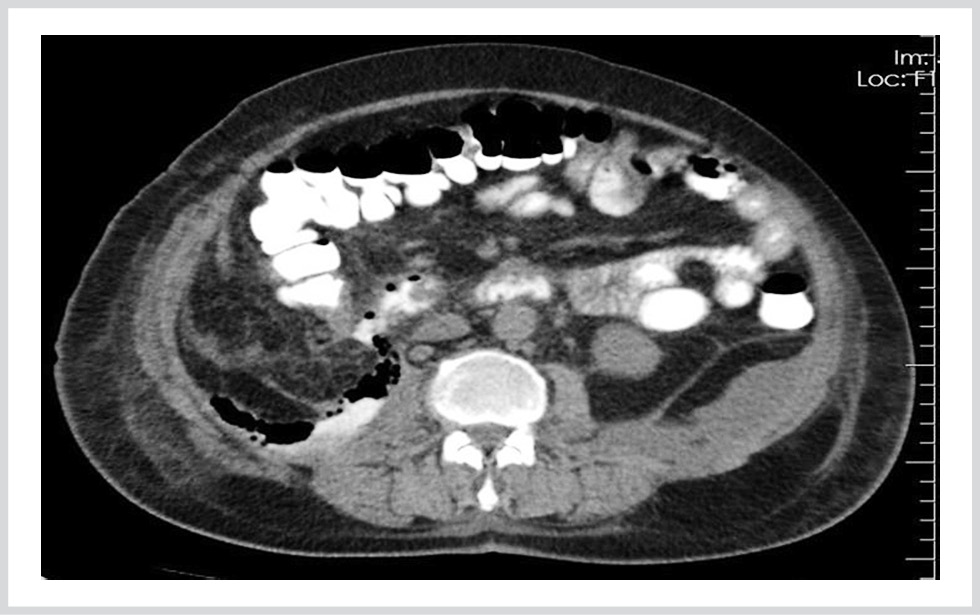
Fig. 1. Extravasation of orally administered contrast medium from the duodenal defect into a mass within the right retroperitoneal region was observed.
Laboratory results on 17.01.2022 showed elevated CRP (141.6 mg/L), creatinine (103 µmol/L), ESR (105 mm/h), platelets (520·109/L), leukocytes (13.0·109/L), and decreased hemoglobin (6.7 g/dL). A repeat CT scan on the same day revealed a well-demarcated fluid mass (22 mm) with air bubbles in the right retroperitoneal region, significant peritoneal thickening, and surrounding adipose tissue edema. The patient underwent a second percutaneous drainage procedure on 18.01.2022 and continued outpatient care.
On 23.03.2022, the patient was admitted to the intensive care unit with postoperative duodenal perforation, functional fistula, retroperitoneal abscess, and sepsis. Laboratory results at admission included CRP 129.6 mg/L, albumin 3.56 g/dL, hemoglobin 8.0 g/dL, platelet count 584·109/L, and ESR 91 mm/h.
A CT scan on 28.03.2022 revealed a 45-mm retroperitoneal abscess extending from the subdiaphragmatic area to the iliac region and descending along the lumbar muscle, with air bubbles present. Oral contrast extravasation into the retroperitoneal space was noted on the right. Additional focal abscesses with air bubbles were identified on the anterior and lateral bladder walls in the left iliac region and pelvis, with the drainage tube tip visible anterior to the bladder (Fig. 2).
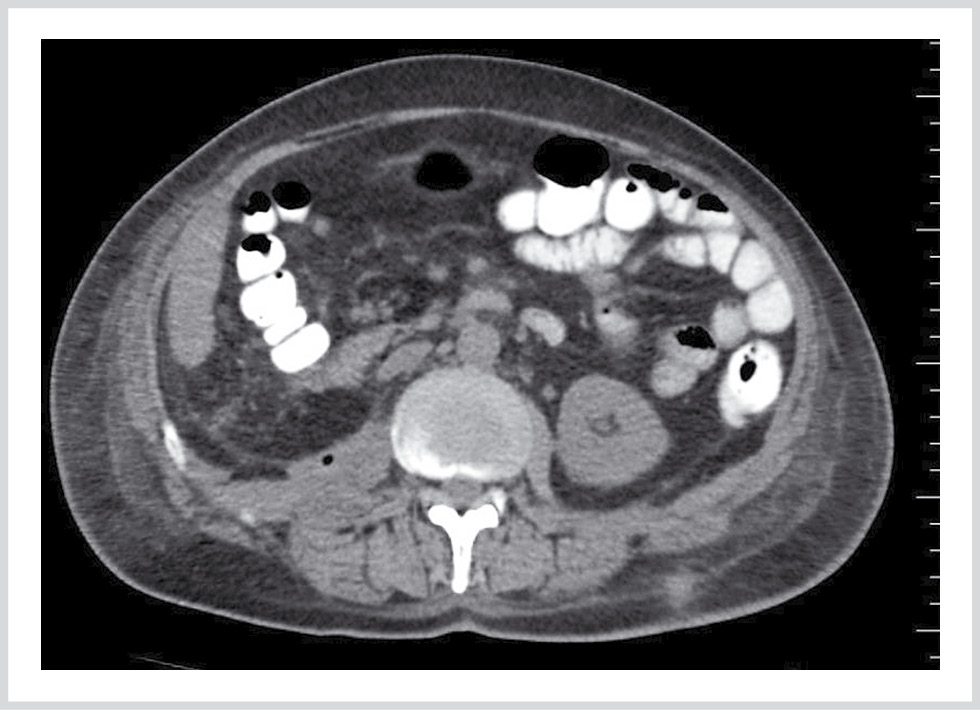
Fig. 2. Extravasation of the oral contrast agent into the retroperitoneal space was observed.
Despite five months of conservative treatment, including two percutaneous drainages, no attempt had been made to close the fistula prior to presentation at our center on 09.04.2022. Endoscopic examination revealed a 0.4×0.6 cm fistula surrounded by granulation tissue on the posterior wall of the second duodenal segment (Fig. 3). TTS endoclips (Olympus, Japan) were applied along the edges of the fistula (Fig. 4, a), and compression with an endoloop (Olympus, Japan) successfully achieved fistula closure (Fig. 4, b, c). One month later, repeat endoscopy confirmed complete fistula closure with scar formation (Fig. 5). A follow-up CT scan with oral contrast on 01.05.2022 showed no contrast extravasation or retroperitoneal leakage, although fibrotic tissue was observed around the duodenum (Fig. 6).
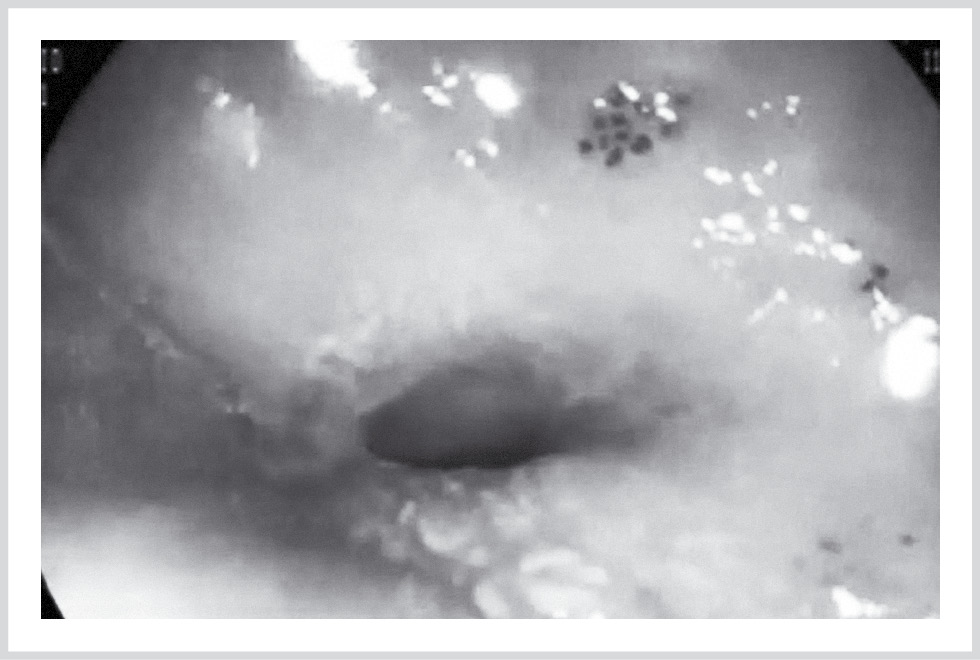
Fig. 3. A fistula tunnel was identified in the posterior wall of the duodenum.
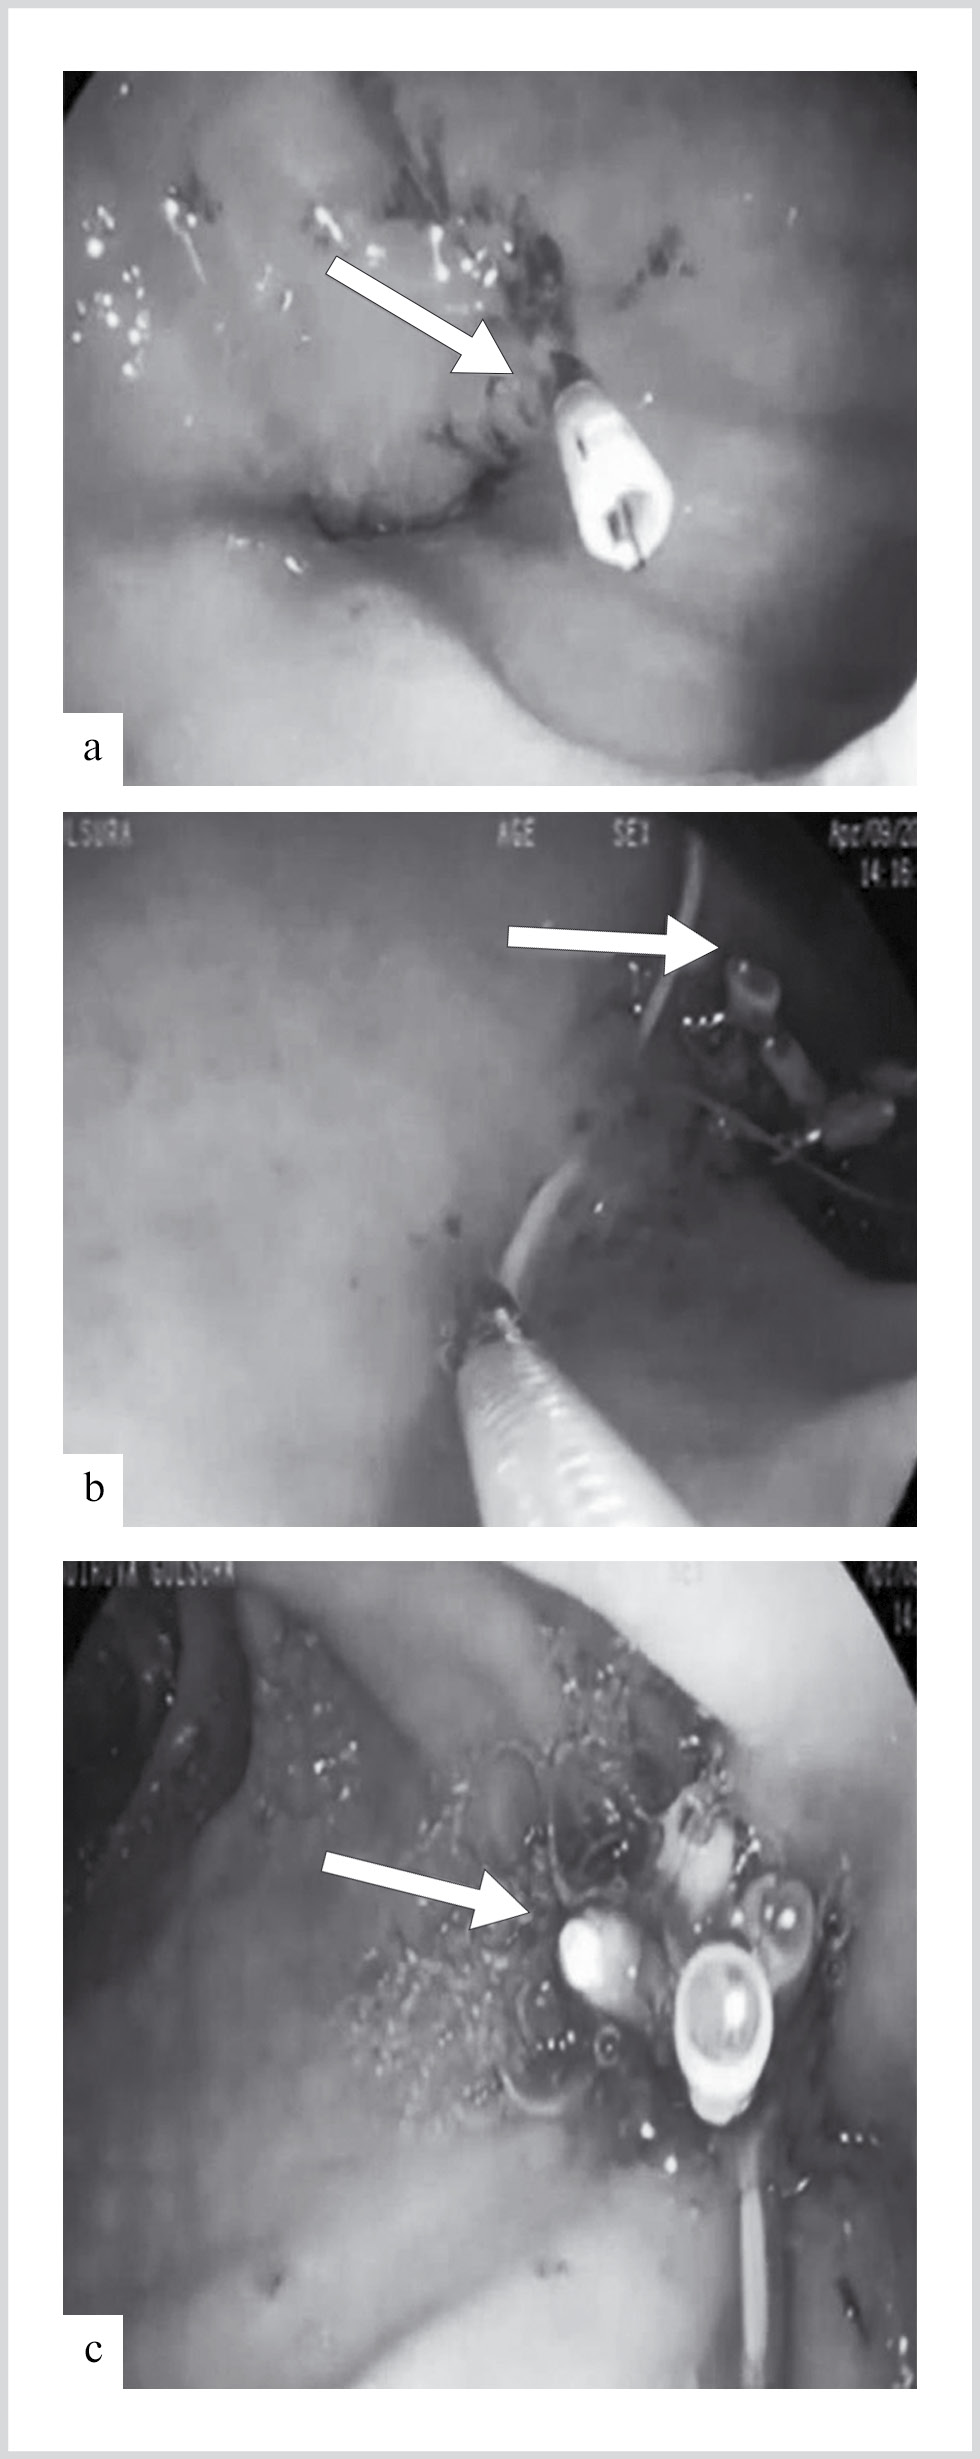
Fig. 4. Stages of endoscopic closure using TTS clips applied to the edges of the fistula (a—c).
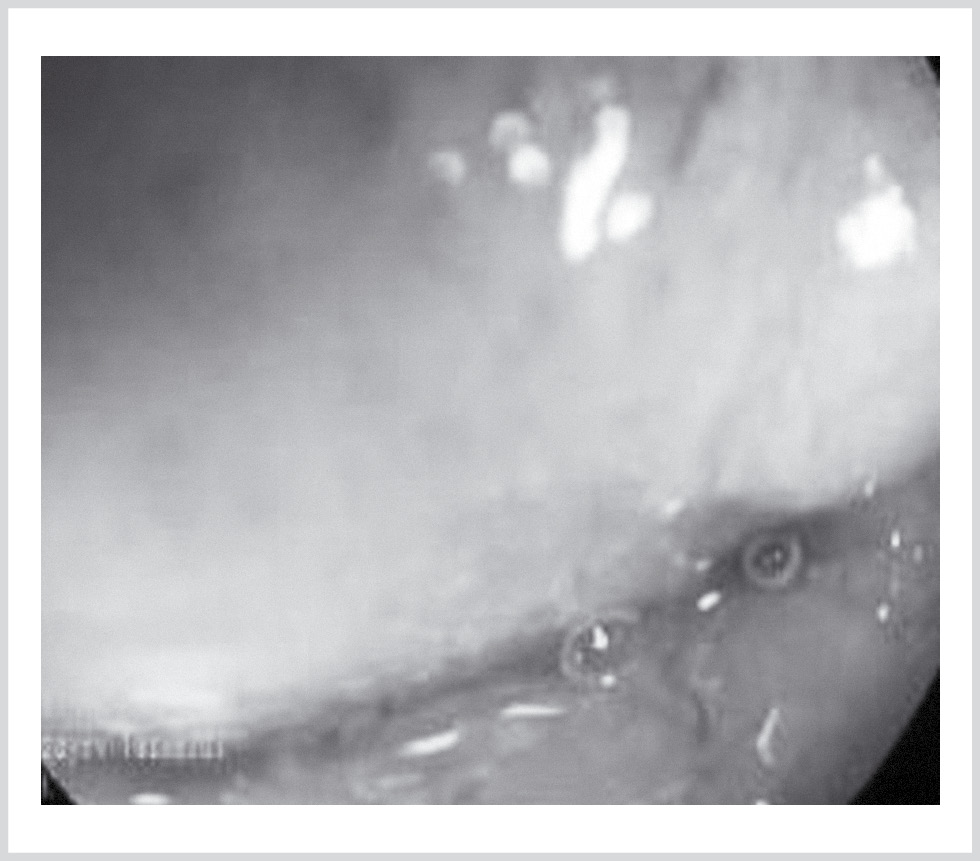
Fig. 5. Scar tissue at the site of the opening of the fistula on the posterior wall of the duodenum.
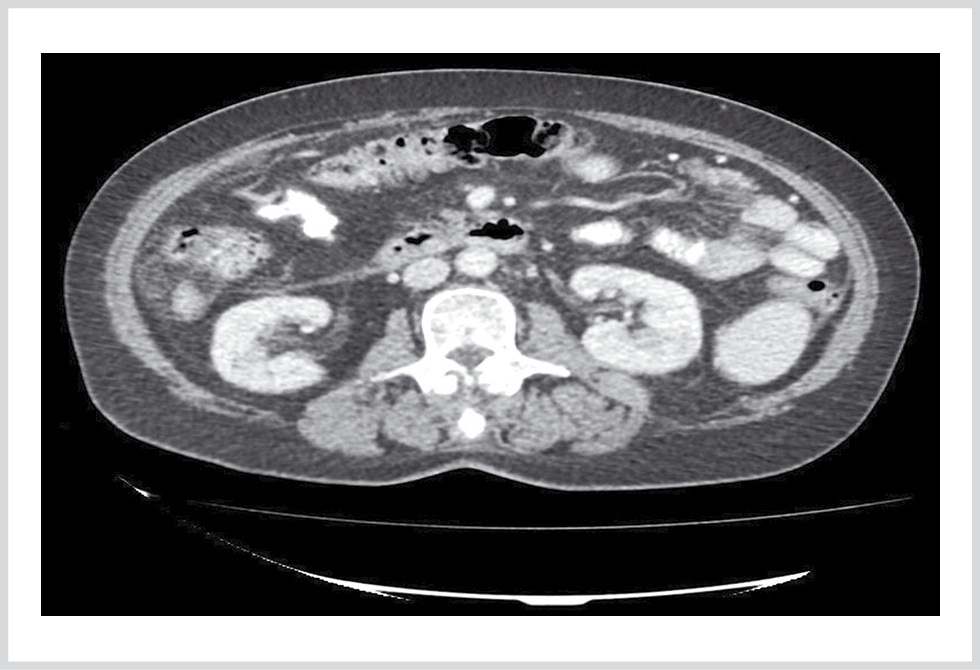
Fig. 6. Contrast-enhanced CT of the abdomen showing fibrous thickening extending from the second segment of the duodenum to Gerota’s fascia in the retroperitoneal region, with no extravasation of oral contrast observed.
Discussion
Duodenal perforation (DP) can result from various causes, including duodenal diverticulum, ischemia, infectious and autoimmune diseases (such as Crohn’s disease, scleroderma, and vasculitis), malignancies, chemotherapy, and gallstone disease [1, 2]. Iatrogenic DP typically occurs due to improper surgical techniques, particularly during tissue dissection [3, 4]. This complication is most commonly observed after laparoscopic procedures, with an incidence of 0.015% [5, 6]. Coagulation necrosis of the duodenal wall may occur due to excessive cauterization, and perforation is often not detected intraoperatively. Symptoms typically manifest several days postsurgery [7, 8].
Treatment for DP includes conservative management, endoscopic intervention, and surgery [9—11]. Concurrently, intensive resuscitation, infection control, and supportive care are essential. While surgical repair can definitively close the perforation, its invasiveness and associated risks are significant drawbacks. In the present case, perforation symptoms emerged 10 days postsurgery, and an endoscopic approach was employed to close the fistula [12, 13].
Endoscopic treatment is a minimally invasive and effective method, particularly when performed within the first 24 hours, before significant inflammatory changes occur in the surrounding tissue [14, 15]. Through-the-scope (TTS) endoclips are highly effective for small duodenal perforations (≤1 cm) [16, 17]. For larger perforations, over-the-scope clips (OTSCs) can grasp more tissue and close defects by compressing all the tissue layers. An OTSC is typically used for perforations between 1-and 3 cm in diameter [18, 19].
In our case, owing to the delayed presentation and the surrounding scar tissue, a TTS clip alone was insufficient for complete closure. Therefore, after placing the endoclips were placed, an endoloop was used to secure them and eliminate any gap between the clips, ensuring reliable and permanent closure. This combined approach was successful in completely sealing the perforation. The use of both endoclips and endoloops allowed for complete closure of the fistula, demonstrating the effectiveness of this technique, which would not have been achieved with endoclips alone.
Funding
This research received no external funding.
Consent for Publication:
The patient provided written informed consent for the publication of any potentially identifiable images included in this article.
Participation of authors:
Concept and design of the study — Rzayev T., Khidirova N.,
Data collection and processing — Rzayev T., Khidirova N., Ibrahimova A., Bayramov N.
Text writing — Rzayev T., Khidirova N., Ibrahimova A.
Editing — Ibrahimova A., Bayramov N.



