
- Media Sphera
- Publishers





Introduction
Minimal residual disease (MRD) in acute myeloid leukemia (AML) is the bone marrow state after initial chemotherapy, comprising residual leukemic cells and regenerating normal hematopoiesis. Its composition carries prognostic information, but extracting it requires a reference frame mapping individual cells onto the hematopoietic hierarchy.
Single-cell transcriptomic atlases provide such a reference. BoneMarrowMap, built on the cellular hierarchy framework of Zeng et al. (2022), comprises 263,159 annotated bone marrow cells spanning 55 fine and 24 broad cell types from 45 healthy donors. A softmax classifier over a 54-dimensional shrinkage-LDA space assigns each query cell a predicted type and confidence maxi pi. The atlas types follow known trajectories: hematopoietic stem cell /multipotent progenitor → lymphoid-primed multipotent progenitor → granulocyte-monocyte progenitor → Monocyte (myeloid); hematopoietic stem cell /multipotent progenitor → megakaryocyte-erythroid progenitor → Erythroblast (erythroid); hematopoietic stem cell /multipotent progenitor → Pro-B → Pre-B → B cell (lymphoid); and so on.
We ask a patient-level question: does the MRD stage distribution, measured along each lineage, differ between patients who will relapse and those who will not? We construct a stage histogram for each patient-lineage pair and compare it to reference histograms from four populations: healthy controls, diagnosis-stage AML, relapsed MRD, and sustained-remission MRD.
Two complementary distances capture histogram similarity: an uncertainty-normalized L1 distance weighting each stage bin by classifier confidence, and an adjacent-stage concordance τNN measuring whether local gradients between consecutive stages agree with the reference. Four references×five lineages×two distances yield a 40-dimensional feature vector per patient that robustly discriminates relapse from sustained remission across cross-validation protocols. In Part II of this work, we develop a complementary toolset of ML models that enhances LDA partitions of the BoneMarrowMap and connects to classification. Part II is more technical and is expected to surpass the distribution-based approach of Part I when significantly more data becomes available.
Methods
Reference atlas and classifier
BoneMarrowMap: 263,159 bone marrow cells from 45 healthy donors, 55 fine/24 broad types. A classifier trained by SGD in a 54-dimensional shrinkage-LDA space (Ledoit—Wolf regularized, 55 classes), stage-sequence agnostic, achieved 95% held-out accuracy.
Developmental lineages and stage assignment
The 24 broad cell types were organized into five hematopoietic lineages based on established developmental relationships (Fig. 1).

Fig. 1. Five hematopoietic lineage chains defined by the BoneMarrowMap atlas.
Each chain follows the established developmental ordering from HSC/MPP to a terminally differentiated cell type. HSC — hematopoietic stem cell, MPP — multipotent progenitor, LMPP — lymphoid-primed multipotent progenitor, GMP — granulocyte-monocyte progenitor, MEP— megakaryocyte-erythroid progenitor, cDC — conventional dendritic cell, pDC — plasmacytoid dendritic cells.
Each query cell was assigned to a lineage based on its predicted broad type. Cells whose predicted type appears in multiple lineages (e.g., hematopoietic stem cell /multipotent progenitor is shared across all five) contribute to each (see Fig. 1). The stage histogram for a patient-lineage pair is the vector of fractions: hk=(number of cells at stage k)/(total cells in that lineage), for k=1, …, K.
Reference populations
Four reference histograms were computed for each lineage by averaging the stage histograms across patients in each group:
Control: 38 healthy donor samples from 8 cohorts (Bailur, Lasry, Petti, Rodríguez-Meira, van Galen, Zeng, Gawad, Beneyto-Calabuig).
Diagnosis: 272 AML patient samples at initial diagnosis from 21 cohorts.
Relapsed MRD: MRD-phase samples from patients who subsequently relapsed.
Sustained MRD: MRD-phase samples from patients with no recorded relapse.
In cross-validation, relapsed and sustained references were recomputed per fold (training set only); control and diagnosis references were held fixed.
Distance measures
For each patient at MRD, with stage histogram h=(h1, …, hk) and per-stage classifier confidence c=(c1, …, ck), where ck is the mean confidence of cells assigned to stage k:
Uncertainty-normalized L1 distance
,
 ,
where H is a reference and ε=0.05. Differences in high-confidence stages are amplified; low-confidence differences dampened.
Adjacent-stage concordance
.
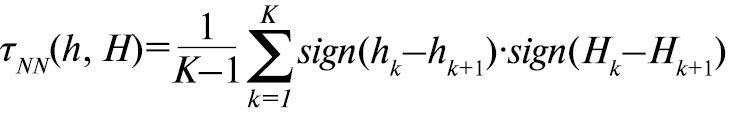 .
This measures whether the patient and reference agree on the local gradient between consecutive developmental stages—whether each transition increases or decreases the cell fraction. Unlike the full Kendall τ, which compares all K(K–1)/2) pairs including biologically distant stages (e.g., HSC/MPP vs. Monocyte), the adjacent-stage concordance focuses on the K–1 transitions that correspond to actual developmental steps in the lineage chain. A patient whose local gradients match the relapsed reference (τNN≈+1) but disagree with the sustained reference (τNN≈–1) is classified as likely to relapse, regardless of how far the absolute fractions differ.
Feature vector
Each patient at MRD is represented by 4×5=20 uncertainty-normalized distances (4 references ×5 lineages) and 4×5=20 adjacent-stage concordance coefficients, for a total of 40 features.
Classifier
Logistic regression with balanced class weights and l2 regularization (C=0.5) was applied to the 40-dimensional feature vector. All features were standardized (zero mean, unit variance) using training-set statistics at each cross-validation fold.
Datasets
Single-cell RNA sequencing data for 47 AML patients with MRD-phase samples and known relapse status were drawn from four cohorts in the Zeng et al. (2025) compendium:
— Ennis et al. (2023): 7 patients (7 relapsed, 0 sustained)
— Lambo et al. (2023): 24 patients (20 relapsed, 4 sustained)
— Naldini et al. (2023): 12 patients (1 relapsed, 11 sustained)
— Beneyto-Calabuig et al. (2023): 4 patients (0 relapsed, 4 sustained)
Patients were labeled “relapsed” if a relapse-phase sample existed and “sustained” otherwise (right-censored).
Cross-validation protocols
Four cross-validation protocols of increasing stringency were applied:
1. Leave-one-out (LOO): Train on N–1 patients, predict 1. All N rotations.
2. Leave-two-out (L2O): Train on N–2, predict 2. 200 randomly sampled pairs from ()=0.081.
 )=0.081.
3. Leave-five-out (L5O): Train on N–5, predict 5. 200 random draws.
4. Repeated 70/30 splits: 200 stratified random splits with 70% train, 30% test.
At each fold, the relapsed and sustained reference histograms were recomputed from the training set. AUC was computed on pooled predictions (L2O, L5O) or averaged across splits (70/30).
Results
Developmental stage distributions differ between clinical phases
Table 1 shows the mean fraction of cells at each developmental depth across clinical phases, aggregated over all lineages. MRD populations are shifted toward terminal differentiation (70% mature) relative to both diagnosis (33%) and healthy controls (52%), with relapsed MRD showing greater terminal enrichment (74%) than sustained MRD (64%). The per-lineage stage distributions are shown in Fig. 2.
Table 1. Broad developmental stage fractions by clinical phase (mean across patients)
| Phase | n | Primitive | Progenitor | Terminal |
|---|---|---|---|---|
| Control | 38 | 0.244 | 0.232 | 0.523 |
| Diagnosis | 272 | 0.244 | 0.428 | 0.328 |
| MRD — sustained | 19 | 0.155 | 0.208 | 0.637 |
| MRD — relapsed | 28 | 0.044 | 0.219 | 0.737 |
Primitive: HSC/MPP and early multipotent progenitors. Progenitor: committed and late progenitors. Terminal: mature and terminally differentiated cells.

Fig. 2. Developmental stage distributions by clinical phase and outcome for each of the five lineages.
Each panel shows the mean fraction of cells at each developmental stage for four groups: healthy Control, AML Diagnosis, MRD Relapsed, and MRD Sustained. Within each group, bars are arranged from early (light) to late (dark) developmental stages. Error bars show standard error of the mean; n indicates the number of patients in each group. Fractions are renormalized per patient before averaging. The progression from diagnosis (early-dominated) through MRD Relapsed (terminal-dominated) is visible in every lineage, while MRD Sustained closely tracks healthy Control.
Per-lineage stage profiles identify discriminative signatures
The dendritic lineage carries the strongest per-lineage signal. At MRD, relapsed patients have significantly higher plasmacytoid dendritic cell fractions (0.281 vs. 0.150, Mann—Whitney p=0.003) and conventional dendritic cell fractions (0.323 vs. 0.175, p=0.003) than sustained patients. In the myeloid lineage, the Monocyte fraction is elevated in relapse (0.374 vs. 0.235, p=0.0006). Table 2 summarizes the mature cell fractions across all lineages.
Table 2. Mature cell fractions at MRD by outcome and in healthy controls
| Lineage | Terminal type | Control | Relapsed | Sustained |
|---|---|---|---|---|
| Myeloid | Monocyte | 0.259 | 0.374 | 0.235 |
| Erythroid | Late Erythroid | 0.379 | 0.505 | 0.249 |
| B-cell | B + Plasma Cell | 0.344 | 0.270 | 0.255 |
| T/natural killer | CD4 + CD8 Memory T | 0.413 | 0.527 | 0.461 |
| Dendritic | cDC + pDC | 0.470 | 0.604 | 0.325 |
Each value is the fraction of cells within the corresponding lineage that are classified as the terminal cell type
Relapsed MRD exceeds the healthy control fraction for Monocyte, Late Erythroid, Memory T, and dendritic cells. Sustained MRD falls below the control fraction for all lineages except T/natural killer. The pattern is consistent: relapsed MRD populations are over-mature relative to control; sustained MRD populations are under-mature. Both comparisons are visible in Fig. 2.
Uncertainty normalization improves classification
Table 3 compares three histogram distance measures on the same 4-reference, 5-lineage feature structure with LOO (Leave-One-Out ) evaluation.
Table 3. Effect of distance measure on classification performance (LOO AUC, 47 patients).
| Distance measure | AUC |
|---|---|
| L1 unweighted | 0.805 |
| L1confidence-weighted | 0.842 |
| L1uncertainty-normalized | 0.889 |
All models use 20 distance features (4 references×5 lineages)
Per-stage confidence varies: plasmacytoid dendritic cells have mean confidence 0.90 (relapsed) vs. 0.62 (sustained), while LMPP sits at ~0.4 in both groups. Inverse-uncertainty weighting amplifies the reliable pDC difference and dampens the noisy LMPP one.
Adjacent-stage concordance adds orthogonal information
Adding within-lineage adjacent-stage concordance τNN to the uncertainty-normalized distances improves AUC from 0.889 to 0.949, table 4. This orthogonal property captures whether the patient’s local developmental gradients match the reference, independently of the magnitudes. A patient can have a histogram close to the relapsed reference in absolute terms but with inverted local gradients—the τNN catches this. Restricting the concordance to adjacent stages (rather than all pairs as in the full Kendall τ) improves performance because the biologically meaningful comparisons are between consecutive developmental stages; comparisons between distant stages (e.g., HSC/MPP vs. Monocyte) are trivially concordant and add noise.
Table 4. Classification performance across cross-validation protocols. du: uncertainty-normalized distances (20 features).
| Model | Features | LOO | L2O | L5O | 70/30 |
|---|---|---|---|---|---|
| du only | 20 | 0.889 | 0.899 | 0.876 | 0.872±0.091 |
| du+τNN | 40 | 0.949 | 0.926 | 0.952 | 0.922±0.073 |
τNN: within-lineage adjacent-stage concordance (20 features)
The improvement is consistent across all four protocols, Table 4. The L5O AUC (0.952) exceeds the LOO AUC (0.949), indicating no overfitting: the model generalizes when five patients are held out simultaneously (Fig. 3).

Fig. 3. Classification performance.
a — receiver operating characteristic curves for the distance-only model (20 features, blue) and the combined distance + τNN model (40 features, red), both evaluated by leave-one-out; b — AUC comparison across four cross-validation protocols of increasing stringency.
Fig. 4 shows the per-patient leave-one-out predictions. Misclassified patients (black outlines) cluster near the decision boundary at P(relapse)=0.5.

Fig. 4. Per-patient leave-one-out predictions from the du+τNN model (40 features).
Each bar represents one patient, colored by true outcome (red: relapsed, blue: sustained). Bars with black outlines indicate misclassifications. Patient identifiers are shown for misclassified cases.
The developmental ordering is a structural prior, not an empirical optimum
We permuted stage ordering within each lineage (50 random permutations) and recomputed LOO. Since du is permutation-invariant, the AUC difference comes entirely from τNN.
True ordering: AUC 0.949. Random permutations: 0.914±0.033 (range 0.829–0.981); 9/50 exceeded the true ordering. With 47 patients, some lucky orderings overfit, but the atlas ordering is a reliably good prior: it gains +0.060 over distance-only, vs. +0.025 on average for random orderings, and generalizes because it reflects external biology.
Cross-lineage correlations are real but redundant for classification
Per-donor analysis of BoneMarrowMap (45 donors) reveals cross-lineage correlations of mature fractions: myeloid×T/NK p=0.86, myeloid×dendritic p=0.51, myeloid×dendritic p=0.33 (Spearman, p<0.05). These persist at MRD (myeloid×T/NK p=0.82 in relapsed). The lineages share a common HSC/MPP root; their deviations are correlated across patients.
Yet cross-lineage concordance features do not improve classification: pairwise mature-fraction concordance across all 10 pairs (AUC 0.876), top-3 pairs (0.910), full stage×stage across all pairs (0.870), and top-3 pairs (0.949, matching baseline). In every case cross-lineage features degraded or added nothing.
The explanation is redundancy, not independence: each within-lineage feature already captures its share of the common HSC/MPP perturbation. The five lineages are corroborating witnesses to the same event; the classifier gains nothing from knowing they agree.
Discussion
Our central observation: the developmental stage distribution within each lineage—the analog of an age distribution in an interacting population (Esipov, Salueña, 2020) — carries prognostic information at MRD. Just as a forest stand’s diameter distribution follows a characteristic geometric decay (de Liocourt, 1898) and shifts predictably under disturbance (Laurance et al., 2004), the stage histogram of a hematopoietic lineage reflects the rates at which cells transition from primitive to mature states. Relapsed patients have distributions skewed toward terminal differentiation; sustained-remission patients retain a more balanced, control-like profile.
The five lineages are correlated (p=0.82 myeloid×T/NK in relapsed MRD), yet cross-lineage features add nothing beyond within-lineage histograms. This signature points to a shared root cause with independent downstream propagation: a perturbation at HSC/MPP sets the initial condition, each chain then runs its own dynamics. The correlation confirms the common origin; the redundancy confirms the absence of inter-lineage coupling. All five lineages shift toward accelerated maturation at MRD in relapsed patients. Under a steady-state assumption, adjacent stage-fraction ratios give transition-rate ratios; at each commitment step (LMPP→Early GMP, MEP→Early Erythroid, HSC/MPP→Early Lymphoid), relapsed patients show 2–4×faster transitions than controls. This lineage-independent acceleration from the shared HSC/MPP compartment is consistent with a cell-intrinsic alteration—most parsimoniously, a pre-leukemic chromatin-regulator mutation (DNMT3A, TET2, ASXL1, IDH1/2) modifying differentiation kinetics without detectable CNV, invisible to inferCNV-based annotation.
Cross-referencing our classifier’s predicted cell types with the independent Normal-versus-Malignant annotation in the Lambo et al. (2023) cohort—the only cohort with complete annotation—confirms that the excess mature cells at MRD are overwhelmingly normal, not malignant. In 23 of 24 Lambo patients, Monocytes and plasmacytoid dendritic cells at MRD are 100% Normal by inferCNV. The over-maturation signature therefore reflects aberrant regeneration of normal hematopoiesis, not transcriptional mimicry by residual blasts. A single exception, AML21, shows 99% Malignant monocytes—genuine mimicry—and is notably the patient our classifier struggles with most across all model variants.
Sustained-remission patients tell the complementary story: their MRD distributions are closer to control, suggesting the disease/treatment perturbation heals during recovery. Relapsed distributions diverge from control—a divergence already measurable at MRD, before clinical relapse.
Taken together, these results identify developmental over-maturation across hematopoietic lineages as a quantifiable signature of relapse risk at MRD (leave-one-out AUC 0.95). The signature is measurable from standard single-cell RNA sequencing and a public reference atlas, requiring no trajectory inference, genetic input, or specialized assays.
Limitations
Exploratory analysis
This is pattern discovery on small cohorts, not a validated clinical tool. 47 patients (28 relapsed, 19 sustained) from four cohorts yield AUC estimates with standard deviation ~0.07 across repeated splits. The consistency across cross-validation protocols (LOO 0.949, L2O 0.926, L5O 0.952, 70/30 0.922) and the absence of overfitting (L5O exceeds LOO) are encouraging,; prospective validation on an independent, uniformly processed cohort is required before clinical use.
Right-censoring
Patients labeled as “sustained” had no relapse sample in the compendium, but some may relapse after data collection.
Cohort imbalance
The four cohorts contribute unevenly to the two outcome groups: Ennis et al. (2023) provides 7 relapsed and 0 sustained; Naldini et al. (2023) provides 1 relapsed and 11 sustained. Leave-one-out and leave-two-out cross-validation mix patients across cohorts in every fold, mitigating but not eliminating cohort-specific batch effects.
Atlas dependency
All assignments depend on BoneMarrowMap; systematic atlas biases propagate to the histograms. Within-patient longitudinal comparisons are robust; cross-cohort comparisons may be affected by differing gene overlap with the atlas.
Acknowledgment
We thank Andy G.X. Zeng and John E. Dick for providing access to the AML single-cell compendium that made this study possible. The BoneMarrowMap reference atlas is available at https://github.com/andygxzeng/BoneMarrowMap.
1This work was carried out through intensive collaborative sessions with the AI co-author (Claude Opus 4.6, Anthropic), whose ability to write, debug, and iterate analysis code in real time made the scope of this study feasible for a human researcher.



